| |
| Alle Journale wurden nach female durchsucht |
Treffer 1 - 18 von 18 |
|
|
|---|
|
1. Moser W;
Marhold F;
Ungersböck K;
Oberndorfer S
Subacute Spinal Cord Cempression Due to an Intramedullar Spinal Teratoma in a 53-Year-Old Female Patient: A Case Report
Spinal Teratoma
European Association of NeuroOncology Magazine 2014; 4 (1): 34-36
MRI of the thoracic and lumbar spine after partial resection. Keywords: MRI,
spinal teratoma
|
|
|
2. Moser W;
Marhold F;
Ungersböck K;
Oberndorfer S
Subacute Spinal Cord Cempression Due to an Intramedullar Spinal Teratoma in a 53-Year-Old Female Patient: A Case Report
Spinal Teratoma
European Association of NeuroOncology Magazine 2014; 4 (1): 34-36
Intraoperative pictures: (a) after opening of the dura mater; (b) pus-like liquid appearing during
resection of the tumour; (c) collapse of the myelon
after resection. Keywords: intraoperative picture,
photograph,
spinal teratoma
|
|
|
3. Moser W;
Marhold F;
Ungersböck K;
Oberndorfer S
Subacute Spinal Cord Cempression Due to an Intramedullar Spinal Teratoma in a 53-Year-Old Female Patient: A Case Report
Spinal Teratoma
European Association of NeuroOncology Magazine 2014; 4 (1): 34-36
MRI of the thoracic and lumbar spine at admission, showing the teratoma at levels Th11/Th12. Keywords: MRI,
spinal teratoma
|
|
|
4. Jaursch-Hancke C
Androgenmangel bei Frauen: Wann klinisch relevant?
Androgenmangel - Frau
Journal für Klinische Endokrinologie und Stoffwechsel - Austrian Journal of Clinical Endocrinology and Metabolism 2011; 4 (3): 12-16
Klinische Symptomatik des Androgenmangels bei Frauen („ Female Androgen Insufficiency Syndrome“ [FAIS], „Hypoactive Sexual Desire Disorder“ [HSDD]). Keywords: Androgenmangel,
Diagramm,
Endokrinologie,
Frau
|
|
|
5. Bals-Pratsch M;
Bühler K;
Krüssel J;
Wendelken M;
Dahncke W;
Kupka MS
Extended Analyses of the German IVF Registry (DIR): Andrological Aspects, Medical-Economical Assumptions Related to the Shift from IVF to ICSI and Stimulation with Gonadotropins
IVF - ICSI
Journal für Reproduktionsmedizin und Endokrinologie - Journal of Reproductive Medicine and Endocrinology 2010; 7 (1): 40-44
Percentage of IVF (line with filled circle) and ICSI (line with filled quad) cycles
(n = 488,174) performed plotted against the female age (1998–2008), means for percentage
of IVF and ICSI treatments are marked by solid lines. |
|
|
6. Geisthövel F;
Wacker A;
Brabant G;
Botsch F;
Maechtel A;
Wetzka B;
Ochsner A
Novel Systematics of Nomenclature and Classification of Female Functional Androgenization (Including Polycystic Ovary Syndrome and Non-Classic Congenital Adrenal Hyperplasia)
Box plots
Journal für Reproduktionsmedizin und Endokrinologie - Journal of Reproductive Medicine and Endocrinology 2010; 7 (1): 6-26
Box plots of serum lipids, the major secondary (facultative) variable, in all groups of patients with functional androgenization.
For legend see Figure 2. Dotted lines represent the respective cut-off values: triglycerides (150 mg/dL), high density lipoprotein (HDL)-cholesterol (50 mg/dL).
Statistically significant differences are:
Triglycerids:
FCA vs. III, IV 0.0021, 0.0301
FAS I vs. III, IV < 0.0001, 0.0161
FAS III vs. II, C 0.0014, 0.0003
HDL :
FAS I vs.II–IV 0.0306, < 0.0001, 0.0003
FAS III vs. FCA, C 0.0173, 0.0001
FAS IV vs. C 0.0030 |
|
|
7. Geisthövel F;
Wacker A;
Brabant G;
Botsch F;
Maechtel A;
Wetzka B;
Ochsner A
Novel Systematics of Nomenclature and Classification of Female Functional Androgenization (Including Polycystic Ovary Syndrome and Non-Classic Congenital Adrenal Hyperplasia)
Box plots
Journal für Reproduktionsmedizin und Endokrinologie - Journal of Reproductive Medicine and Endocrinology 2010; 7 (1): 6-26
Box plots of selected major primary (classifying) variables in all groups of patients with functional androgenization. Results of classification of functional androgenization
summarizing full-blown and minimum standard core/miscellanous clusters (subgroups a and b, respectively). Statistically significant differences among the groups are shown
in detail in Table 8.
FCA: functional cutaneous androgenization; FAS: functional androgenizing syndrome. Insulin 1: 1-h post-load insulin. Results are shown as median (line within in the box), mean
(dot within the box), 75th and 25th percentiles (upper and lower limits of the box), maximum observation below upper fence ( ), minimum observation above lower fence (⊥) and
maximum observation (□). Dotted lines represent the respective cut-off values: LH (8.4 mIU/mL), testosterone (2.1 nmol/L), free androgen index (5), serum insulin 1 (723 pmol/
L). |
|
|
8. Geisthövel F;
Wacker A;
Brabant G;
Botsch F;
Maechtel A;
Wetzka B;
Ochsner A
Novel Systematics of Nomenclature and Classification of Female Functional Androgenization (Including Polycystic Ovary Syndrome and Non-Classic Congenital Adrenal Hyperplasia)
Female androgenization
Journal für Reproduktionsmedizin und Endokrinologie - Journal of Reproductive Medicine and Endocrinology 2010; 7 (1): 6-26
Nomenclature and algorithm of classification of female androgenization. Diagnostic level I is the screening
step regarding clarification of functional androgenization (FA), and/or of cycle irregularities, and/or of infertility, particularly
in the combination with obesity (especially in adolescence). If e.g. elevated C19-sex steroid levels or low
SHBG levels are found, diagnostic level II (see Material and Methods) will follow. At least on this step, areas A to C
can be differentiated. In most cases, area A, the FA, will come in consideration. This area can be further divided
through step II into groups FCA (skin) and FAS I (ovary), II (adrenal gland), III (multi-organ FA disordes), and IV (residual
FA dysfunctions/disorders) (see Material and Methods). When very high serum levels of testosterone and/or DEHAS
are found, the dexamethasone test (level III) may be used in order to differentiate a functional adrenal hyperandrogenaemia
(FAS II) from a non-functional androgen excess which might suscpicous for a tumerous androgenization
(Area B) (data not shown). In addition, it has to be clarified on level II (e.g. by pathologic 17-hydroxy progesterone
levels), whether a CYP21A analysis should follow (level III). On the other hand, by an accurate enquiry concerning the
use of medicine just at the beginning of the medical care it will be found out whether area C (pharmaceutical androgenization)
has to be considered.
PFOs: polyfollicular ovaries; DHEAS: dehydroepiandrosterone-sulphate; SHBG: sex hormone-binding globulin; A:
functional androgenization; B: tumorous androgenization; C: pharmacological androgenization; FCA: functional cutaneous
androgenization; FAS: functional androgenizing syndrome. |
|
|
9. Wieacker P
Genetic Aspects of Premature Ovarian Failure
Hypergonadotropic hypogonadism
Journal für Reproduktionsmedizin und Endokrinologie - Journal of Reproductive Medicine and Endocrinology 2009; 6 (1): 17-18
Possible mechanisms of hypergonadotropic hypogonadism in females. (A) In normal ovaries maturation of follicles is beginning at the time of puberty. (B) In case of maturation arrest only primordial or primary follicles are
present. Basic estradiol production of granulosa cells makes breast development possible, but there is a primary amenorrhea. FSHβ-, FSHR- or LHR-mutations can cause such a condition. (C) In secondary POF, maturation of follicles at puberty makes menarche and breast development possible, but early depletion of follicles causes secondary
amenorrhea. Such a condition can be caused by Turner mosaicism. (D) In primary POF, depletion of follicles before the puberty causes primary amenorrhea. Breast development is not possible. (E) In gonadal dysgenesis degeneration of
the follicles occurs during fetal life. In the rule, primary POF and gonadal dysgenesis cannot be delineated clinically. Keywords: POF
|
|
|
10. Markus S;
Hehr U
Genetic Counseling and Testing Prior to Assisted Reproduction
Female Karyotype
Journal für Reproduktionsmedizin und Endokrinologie - Journal of Reproductive Medicine and Endocrinology 2009; 6 (1): 6-10
Female karyotype showing a Robertsonian translocation between chromosomes 13 and 14 (arrow indicates
derivative chromosome resulting from Robertsonian translocation). Keywords: Chromosom,
chromosome,
female karyotype,
Reproduktionsmedizin,
weiblicher Karyotyp
|
|
|
11. Markus S;
Hehr U
Genetic Counseling and Testing Prior to Assisted Reproduction
Female karyotype
Journal für Reproduktionsmedizin und Endokrinologie - Journal of Reproductive Medicine and Endocrinology 2009; 6 (1): 6-10
Female karyotype showing a reciprocal balanced translocation between the short arm of chromosome 1
and the long arm of chromosome 16 (arrows indicate derivative chromosomes). Keywords: Chromosom,
chromosome,
female karyotype,
Reproduktionsmedizin,
weiblicher Karyotyp
|
|
|
12. Fancsovits P;
Takacs FZ;
Tothne GZ;
Papp Z;
Urbancsek J
Examination of Early Cleavage an its Importance in IVF Treatment
First Cell Cycle
Journal für Reproduktionsmedizin und Endokrinologie - Journal of Reproductive Medicine and Endocrinology 2006; 3 (6): 367-372
Timing of the first cell cycle of a human zygote. The upper figure line indicates the biological occurrence in oocytes from fertilization to first cleavage. Following sperm penetration, the second meiotic division is completed. After first polar body extrusion, the G1-phase of the first cell cycle begins, in which male and female
pronuclei appear. The G1-phase is followed by the S-phase in which the chromosomes replicate. It is followed by the G2-phase in which DNA synthesis cannot be observed any more. The M-phase of the first cell cycle begins with the disappearance of pronuclei and lasts until completion of the first cell division. 0PN = no pronucleus;
1PB = one polar body; G1, S, G2, M: phases of cell cycle [Author permission granted by P. Fancsovits] Keywords: cell cycle,
Schema,
scheme,
Zellzyklus,
Zygote,
Zygote
|
|
|
13. Zech N
Plasticity of Stem Cells: Cell-fusion Versus Transdifferentiation
Sex mismateched stem cell transplantation
Journal für Reproduktionsmedizin und Endokrinologie - Journal of Reproductive Medicine and Endocrinology 2005; 2 (4): 239-245
Sex mismatched stem cell transplantation to track progeny cells: claims on the plasticity of
stem cells often rely on the appearance of Y-positive cells in female recipients of male bone marrow transplant donors (left). Injection of marked bone marrow cells from female donors into male recipients is more suitable to demonstrate fusion events because marked Y chromosome-positive cells found in the recipient must have been formed by a fusion event (right). Keywords: Geschlecht,
Reproduktionsmedizin,
Schema,
scheme,
sex,
Stammzelle,
stem cell,
transplantation,
transplantation
|
|
|
14. Selb Semerl J;
Kenda MF
Out of Hospital Sudden Cardiac Death Among Physically Active and Inactive Married Persons Younger than 65 Years in Slovenia
Aktivität - Plötzlicher Herztod
Journal of Clinical and Basic Cardiology 2003; 6 (1-4): 63-67
Highest level of physical exertion (Physical Activity Rating Scale) performed by sudden cardiac death victims on the day of death by gender (1: sitting or lying awake; 2: sitting performing easy tasks;
3: very light; 4: light exertion with normal breathing; 5: moderate exertion
with deep breathing; 6: vigorous exertion with panting, overheating; 7: heavy exertion with gasping, much sweating; 8: extreme or peak
exertion). Keywords: Aktivität,
diagram,
Diagramm,
female,
Frau,
gender,
Geschlecht,
Male,
Mann,
physical activity,
plötzlicher Herztod,
sudden cardiac death
|
|
|
15. Ricci S;
Capocaccia R;
Manna P;
Piscicelli C;
Serra GB;
Trimboli A
Hormone Replacement Therapy and Mortality for Ischaemic Heart Disease, Cerebrovascular Diseases and Breast Cancer in Italy and the U.S.A.
Italien - USA - Mortalität
Journal of Clinical and Basic Cardiology 2002; 5 (1): 105-108
Mortality-% of total female deaths in Italy (n = 274,814) and in the U.S.A. (n = 1,160,206) due to ischaemic heart disease (IHD), cerebrovascular diseases (CeVD), and breast cancer (BC), by age decades in women aged 40 and over (1997) Keywords: breast cancer,
Brustkrebs,
Diagramm,
female,
Frau,
heart disease,
Herzkrankheit,
ischaemia,
Ischämie,
Italien,
Italy,
Mammakarzinom,
mortality,
Mortalität,
stroke,
USA,
USA
|
|
|
16. Vormann J;
Anke M
Dietary Magnesium: Supply, Requirements and Recommendations - Results From Duplicate and Balance Studies in Man
Knochen - Magnesiumgehalt
Journal of Clinical and Basic Cardiology 2002; 5 (1): 49-53
Magnesium content of human bone (rib); mean +/- SD, n=10 Keywords: Bone,
Content,
Diagramm,
female,
Frau,
Knochen,
magnesium,
magnesium,
Male,
Mann
|
|
|
17. Salvadori A;
Arreghini M;
Bolla G;
Fanari P;
Giacomotti E;
Longhini E;
Miserocchi G;
Palmulli P
Cardiovascular and adrenergic response to exercise in obese subjects
Herzfrequenz - Adipositas
Journal of Clinical and Basic Cardiology 1999; 2 (2): 229-236
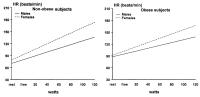
Heart rate (HR) vs. watt relationship in non-obese and obese males and females. The regression lines were: HR = 90.7 + 0.7 watt - 14.2Z2 - 0.2 wattZ2 (R2: 0.8; F: 205; MSE: 248) in the control group, and: HR = 98 + 0.6 watt - 5.8Z2 - 0.2 wattZ2 (R2: 0.8; F: 180; MSE: 145) in the obese group, with a dummy variable Z2 = 1 for males and 0 for females because the two regression lines have significantly different slopes (P < 0.001) Keywords: Adipositas,
Belastung,
Diagramm,
exercise,
heart rate,
Herzfrequenz,
Leistung,
obesity
|
|
|
18. Salvadori A;
Arreghini M;
Bolla G;
Fanari P;
Giacomotti E;
Longhini E;
Miserocchi G;
Palmulli P
Cardiovascular and adrenergic response to exercise in obese subjects
Sauerstoffverbrauch - Adipositas
Journal of Clinical and Basic Cardiology 1999; 2 (2): 229-236
Oxygen consumption (V·O2) vs. watts relationship in nonobese and obese males and females. The regression lines were: V·O2 = 363.6 + 11.4 watt + 91.4Z2 (R2: 0.95; F: 1420; MSE: 10445) in the control group, and V·O2 = 615.3 +/- 12 watt (R2: 0.65; F: 93; MSE: 247.6) in the obese group, with a dummy variable Z2 = 1 for males and 0 for females in the regression line of the normal group because the two regression lines are parallel, but not coincident (p < 0.001). Keywords: Adipositas,
Belastung,
Diagramm,
exercise,
Leistung,
obesity,
oxygen consumption,
Sauerstoffverbrauch
|
|
|
| |
|
 Suche Medizinische Publikationen
 Suche Abbildungen und Grafiken
 Medizinprodukte - Labortechnik
 Antidotarium (Stand 2012)
 Phytokodex (Stand 2012)
 Fachbücher
 Patientenliteratur